Ankle Fracture
Surgical treatment of malleolar ankle fractures
Overview
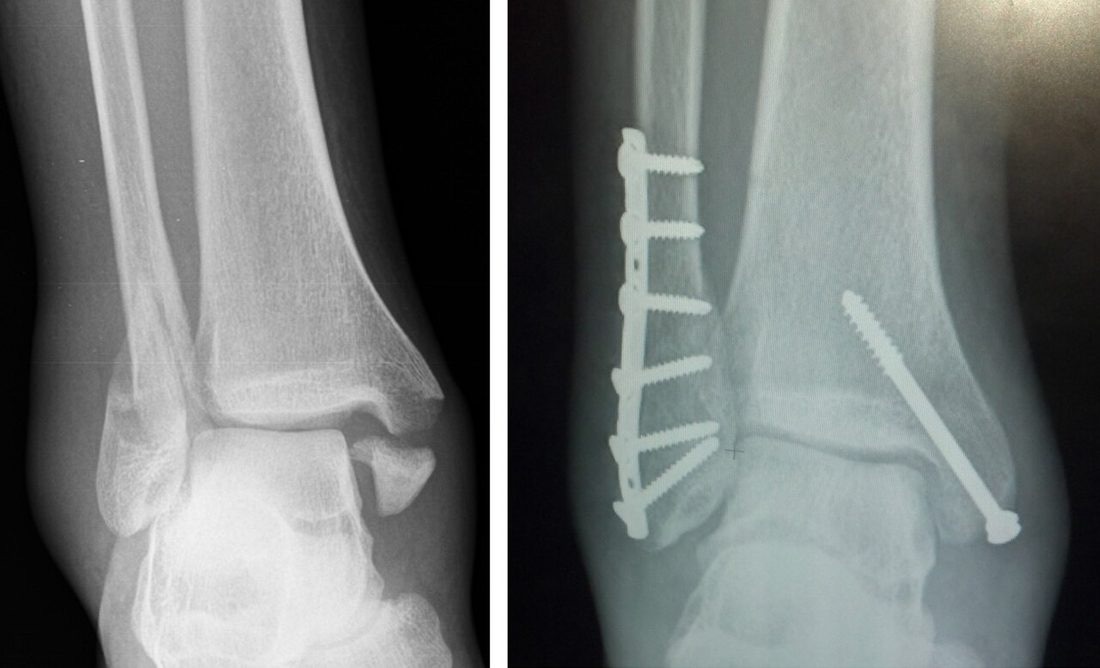
The ankle joint (talocrural joint) is a hinge-type joint formed by three bones: the tibia (shin bone), the fibula, and the talus. The medial malleolus (inner projection of the tibia), the lateral malleolus (outer projection of the fibula) and the posterior malleolus (posterior projection of the tibia) form a ring — the ankle mortise — that surrounds the talus on three sides. Joint stability is provided by bone geometry, the joint capsule, the syndesmotic ligament complex and the medial and lateral collateral ligaments. An ankle fracture is a break in the distal tibia, the distal fibula or the talus. It most often results from an inward or outward twisting injury (inversion/eversion) combined with rotational stress. Ankle fractures are among the most common orthopaedic injuries and occur in every age group.
Classification by Bone Involved
- Isolated lateral malleolus (fibula) fracture: the most common ankle fracture
- Isolated medial malleolus fracture (inner projection of the tibia)
- Posterior malleolus fracture: at the back of the tibia
- Bimalleolar fracture: both medial and lateral malleoli; the ankle is unstable and usually requires surgery
- Trimalleolar fracture: medial, lateral and posterior malleoli; a higher-energy injury
- Pilon (plafond) fracture: a high-energy, comminuted intra-articular fracture involving the weight-bearing surface of the tibia
- Talus fracture: fracture of the talus; uncommon but carries a high risk of avascular necrosis (bone death)
- Maisonneuve fracture: a proximal fibula fracture combined with a medial malleolus fracture or deltoid ligament injury; all syndesmotic ligaments are torn
Weber Classification (by Level of the Fibula Fracture)
- Weber A: below the level of the syndesmosis; generally stable and usually treated non-operatively
- Weber B: at the level of the syndesmosis; stability varies — displacement and associated medial injury determine the need for surgery
- Weber C: above the level of the syndesmosis; syndesmotic injury is common and surgery is usually required
Classification by Displacement and Joint Involvement
- Non-displaced fracture: the bone fragments have not shifted; most are suitable for non-operative treatment
- Displaced fracture: the fragments have shifted; surgical reduction is required
- Intra-articular fracture: the fracture line extends into the joint surface, increasing the long-term risk of arthritis
- Open fracture: the bone has penetrated the skin or there is an open wound over the fracture; infection risk is high and emergency surgery is required
- Stress fracture: hairline fractures caused by repetitive loading or bone loss; seen in athletes and in older patients with osteoporosis
Symptoms
- Sudden, severe pain: at the moment of injury, particularly on weight bearing
- Swelling and bruising: marked oedema and haematoma developing within the first hours
- Inability to bear weight: unable to stand or walk on the leg
- Deformity: visible in displaced fractures
- Tenderness: pain that increases on palpation of the fracture site
- Restricted movement: difficulty bending or extending the ankle
- Altered sensation or coldness: if there is nerve or vascular injury
- Open wound: loss of skin integrity near the fracture in an open fracture
Mechanisms of Injury
- Twisting (sprain) of the ankle — the most common mechanism
- Fall from height
- Sports injuries (football, basketball, skiing, etc.)
- Road traffic accidents (particularly in high-energy pilon fractures)
- Tripping on level ground (especially in older patients with osteoporosis)
- Repetitive loading (for stress fractures)
Diagnosis
Diagnosis is based on a detailed history, physical examination and imaging. Examination assesses swelling, bruising, deformity, points of tenderness (using the Ottawa Ankle Rules — lateral/medial malleolus, navicular and base of the fifth metatarsal), range of motion, syndesmotic tests (squeeze test, external rotation test), neurovascular status and skin integrity.
Plain radiographs are the first-line investigation; anteroposterior, lateral and mortise (15° internal rotation) views are standard. CT is required for surgical planning in intra-articular, comminuted or pilon fractures. MRI is used to assess occult stress fractures, cartilage damage (osteochondral lesions), and syndesmotic and ligament injuries.
Non-operative (Conservative) Treatment
Stable, non-displaced fractures that do not disturb the ankle mortise are suitable for non-operative treatment.
- Isolated non-displaced Weber A and some Weber B fractures
- Non-displaced medial malleolus fractures
- Isolated posterior malleolus fractures without displacement
- Selected stress fractures
- Treatment: a short leg cast or walking boot (ROM walker), on average 6 weeks
- No weight bearing or partial weight bearing initially, as directed by the surgeon
- Ice, elevation and pain control; regular radiographic follow-up; graduated weight bearing and physiotherapy after the cast or boot is removed
Surgical Treatment (ORIF)
Open reduction and internal fixation (ORIF) is the standard treatment for displaced or unstable fractures and for fractures that disturb joint congruity.
- Displaced Weber B–C fractures
- Bimalleolar / trimalleolar fractures
- Syndesmotic instability
- Pilon fractures
- Open fractures
- Athletes and young, active patients in whom anatomical reduction is required
- Treatment: plate and screw fixation (most common); isolated screw fixation; intramedullary nailing (in selected fibula fractures); syndesmotic screw or flexible fixation; external fixation in open fractures; a two-stage approach in pilon fractures
Factors Influencing the Decision to Operate
- Fracture stability (is joint congruity disturbed?)
- Amount of displacement (generally >2 mm favours surgery)
- Presence of syndesmotic injury
- Involvement of the joint surface
- Patient age and activity level
- Bone quality (osteoporosis)
- Soft-tissue condition (swelling, oedema, blisters, open wound)
- Comorbidities (diabetes, peripheral vascular disease, smoking)
Advantages of Surgery
The principal advantage is anatomical restoration of the fracture with rigid fixation. This reduces the long-term risk of mortise disruption, malunion and post-traumatic arthritis.
- Anatomical reduction and early motion; joint stiffness and muscle atrophy are reduced
- Faster return to weight bearing: earlier progression to partial weight bearing may be possible at the surgeon's discretion
- Operative time: 30–60 minutes for simple fractures; 60–120 minutes for bimalleolar/trimalleolar fractures; 2–3 hours or two stages for pilon fractures
- Discharge the following day in appropriately selected patients
- Lower long-term risk of post-traumatic arthritis
Disadvantages of Surgery
- You will need to avoid or restrict weight bearing for 4–6 weeks. Temporary bone loss related to immobilisation (Sudeck's atrophy) may develop during this period; this is entirely reversible and does not occur in every patient.
- There are surgery-specific risks: wound infection, deep infection, superficial nerve sensitivity, implant failure and — very rarely — neurovascular injury.
- Implant irritation: removal of hardware is required in approximately 10–20% of patients.
- Wound healing problems: particularly in pilon fractures, in patients with diabetes and in smokers.
- Joint stiffness may develop during immobilisation, but this resolves completely with physiotherapy.
Expected Outcomes
Most patients with a correctly treated ankle fracture achieve a pain-free, functional ankle. Most return to daily activities within 3–4 months; complete recovery may take up to a year in some cases. Fracture healing takes 6–8 weeks in simple isolated fractures and 10–12 weeks or longer in complex or intra-articular fractures. Intra-articular fractures carry a risk of post-traumatic arthritis, although anatomical reduction and compliant rehabilitation reduce this risk.
Surgery & First 3 Weeks
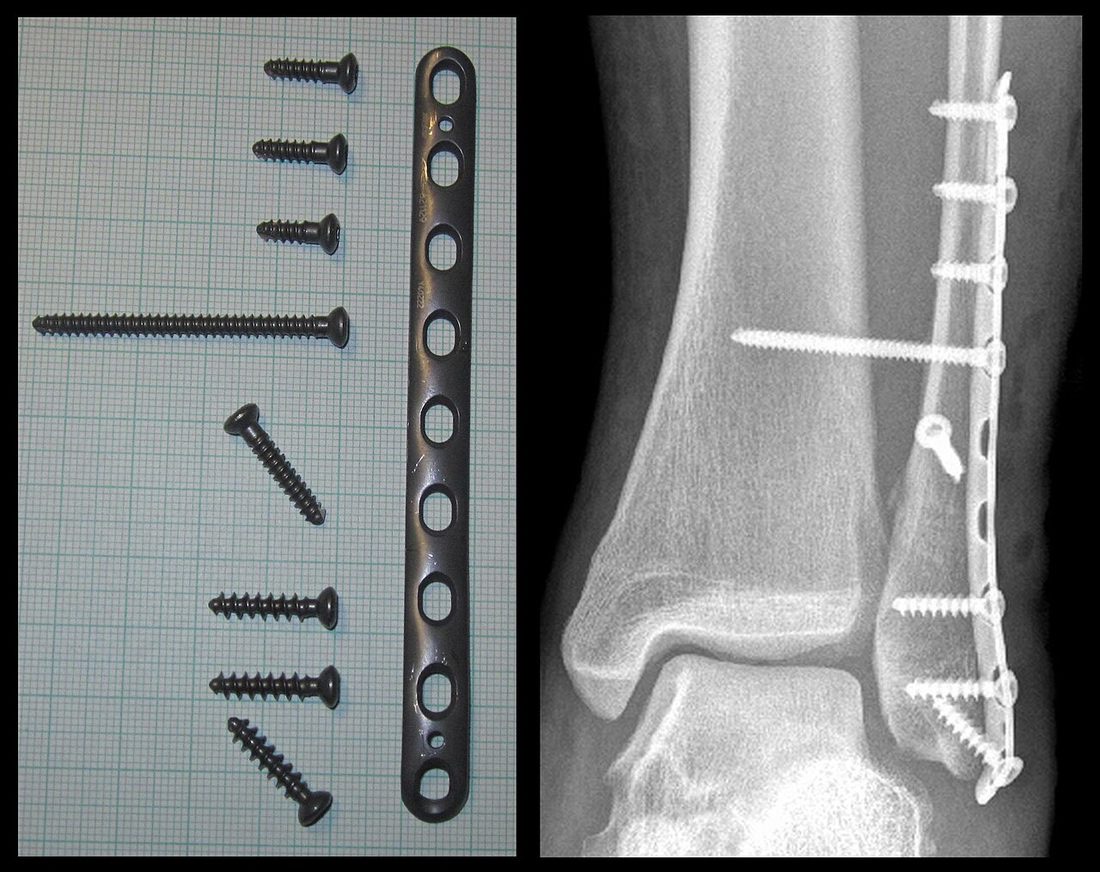
There are two main approaches to the treatment of ankle fractures: non-operative (cast/boot) and surgical (open reduction and internal fixation — ORIF). The choice depends on the fracture type, its stability and patient factors.
Non-operative Treatment
A cast or walking boot (ROM walker) is used for stable, non-displaced fractures.
- Assessment in the emergency department; closed reduction if required (under anaesthesia if necessary)
- Short leg cast (usually the first 2–3 weeks) or walking boot
- No weight bearing for the first 1–2 weeks; thereafter partial to full weight bearing as permitted by the surgeon
- Ice, elevation and analgesia
- Follow-up radiographs at weeks 1, 2, 4 and 6 to monitor for displacement
- Typical duration of immobilisation: 6 weeks
- Graduated weight bearing and physiotherapy once the cast or boot is removed
Surgical Treatment — General Information
Open reduction and internal fixation is performed under spinal/epidural or general anaesthesia. The choice of anaesthetic is made together with the anaesthetist, taking the patient's comorbidities into account. Radiographs and, where required, CT are reviewed for preoperative planning; three-dimensional CT is used for detailed planning in complex pilon fractures.
Prophylactic antibiotics are given before surgery, and a plan for thromboprophylaxis (anticoagulation and compression stockings) is agreed.
- Duration: 30–60 minutes for simple isolated fractures; 60–120 minutes for bimalleolar/trimalleolar fractures; 2–3 hours or two stages for pilon fractures
- Anaesthesia: spinal/epidural or general
- Hospital stay: 1–2 days; longer for pilon and open fractures
Surgical Approaches (Incisions)
The incision is chosen according to the fractured bone and the surgical plan. A single incision may suffice for an isolated fracture, whereas bimalleolar, trimalleolar or pilon fractures may require more than one.
- Lateral approach: for fibula fractures, over the lateral malleolus
- Medial approach: for medial malleolus fractures
- Posterolateral approach: for posterior malleolus or pilon fractures
- Anterior approach: for pilon fractures, to visualise the joint surface directly
- Minimally invasive percutaneous techniques: screws placed through small incisions in selected fractures
Lateral Malleolus (Fibula) Fracture — Technique
The patient is positioned supine or in the lateral decubitus position and a lateral incision is made. The fracture fragments are reduced anatomically and fixed with a one-third tubular or compression plate and screws; an interfragmentary screw is added in some cases. An intramedullary fibular nail is an alternative in osteoporotic or high-risk patients.
Medial Malleolus Fracture — Technique
A medial incision is made. Fixation is typically achieved with two cannulated screws. In small comminuted fractures a K-wire and tension band technique may be used.
Bimalleolar / Trimalleolar Fracture — Technique
Both lateral and medial incisions are made, with a posterolateral incision added if required. The posterior malleolus (if present) is fixed first, then the lateral malleolus and finally the medial malleolus. Fixation is recommended for posterior malleolar fractures involving more than 25% of the joint surface.
Syndesmotic Injury — Technique
Surgical stabilisation is required for a complete tear of the ligament complex between the tibia and fibula. One or two syndesmotic screws (usually 3.5 mm cortical) are used. Flexible fixation systems (suture button / TightRope) are an alternative and do not require screw removal.
Pilon Fracture — Technique
A two-stage approach is generally used. Stage 1: temporary stabilisation with an external fixator, waiting 1–3 weeks for soft-tissue swelling to settle. Stage 2: definitive plate fixation through an anterior or posterolateral approach. The risk of soft-tissue complications is high and surgical planning requires particular care.
Open Fracture
Emergency debridement and irrigation, with antibiotic and tetanus prophylaxis. Depending on the soft-tissue condition, either early definitive fixation or a two-stage approach with temporary external fixation is used.
Discharge Information
Patients are usually discharged after a hospital stay of 1–2 days; a longer stay may be required for pilon fractures. After surgery the ankle is immobilised in a short leg cast or walking boot.
Before discharge, the physiotherapist teaches non-weight-bearing walking with crutches or a frame, transfers, and stair technique. A non-weight-bearing rule applies for the first 4–6 weeks, as directed by the surgeon; early partial weight bearing may be permitted with some stable fixations.
Ice for 15–20 minutes four to five times a day and elevation of the leg are recommended. Analgesics, anti-inflammatories, gastric protection and anticoagulation (for 4–6 weeks or until weight bearing) are prescribed. Compression stockings are worn for the period specified. Sutures are removed on day 14–21.
Early Postoperative Period (First 3 Weeks)
The aims during this period are wound healing, control of swelling, pain management, preserving toe, hip and knee movement, minimising muscle atrophy and maintaining thromboprophylaxis. Weekly review is recommended.
- Wound monitoring: report discharge, marked redness, increased warmth, wound edge separation or malodour immediately
- Swelling control: elevating the leg above heart level, ice and compression stockings reduce swelling
- Weight-bearing protocol: generally no weight bearing for the first 4–6 weeks; early loading increases the risk of implant failure and non-union
- Movement: toe wiggling and hip and knee exercises should be performed daily
- Pain: controlled with prescribed medication, ice and elevation; requirements fall markedly in the first 1–2 weeks
- Thromboprophylaxis: anticoagulation (4–6 weeks), compression stockings, toe movement and hip/knee exercises
- Nerve monitoring: report any numbness or tingling in the toes or dorsum of the foot
Follow-up
- Days 10–14: suture removal and radiographic review
- Weeks 4–6: decision on weight bearing
- Month 3: assessment of bone healing
- Month 6 and annually thereafter if required
Risks & Complications
The treatment of ankle fractures is well standardised in modern orthopaedics and largely produces good results. Nevertheless, both cast treatment and surgery carry specific risks, and it is important that you understand them.
Risks Specific to Non-operative (Cast/Boot) Treatment
- Inadequate reduction / secondary displacement: fragments shifting within the cast; further surgery may be required
- Skin problems: pressure sores, friction and fungal infection beneath the cast
- Joint stiffness: stiffness of the ankle and subtalar joints due to prolonged immobilisation
- Muscle atrophy: weakening of the calf muscles
- Deep vein thrombosis (DVT): risk increased by immobility
- Sudeck's atrophy (temporary bone loss)
Risks Specific to Surgery — Common (Under 5%)
- Superficial wound infection (usually treated with antibiotics)
- Postoperative pain, swelling and temporary bruising
- Temporary joint stiffness — resolves with regular physiotherapy
- Transient symptoms related to anaesthesia such as nausea and dizziness
- Superficial nerve sensitivity (particularly in the superficial peroneal and sural nerve territories)
- Oedema (may be prolonged, persisting for 6–12 months)
Risks Specific to Surgery — Less Common
- Deep infection (osteomyelitis / implant infection): 1–2%; may require revision, implant removal and prolonged antibiotics
- Wound healing problems: common in pilon fractures, in patients with diabetes and in smokers; skin necrosis is rare
- Nerve injury (peroneal, sural, saphenous nerves)
- Vascular injury (very rare)
- Deep vein thrombosis (DVT) and pulmonary embolism (PE): largely prevented by anticoagulation and early toe movement
- Implant failure: loosening or breakage of screws or plates, particularly with early weight bearing
- Compartment syndrome: increasing pain, tightness and loss of sensation in the leg; rare but requires emergency fasciotomy
- Heterotopic ossification (bone formation in soft tissue)
- Complex regional pain syndrome (Sudeck's atrophy)
Long-term Complications
- Malunion: the bone heals in the wrong position, increasing pain and the risk of arthritis
- Non-union: particularly of the medial malleolus; increased by smoking, diabetes, osteoporosis and early weight bearing
- Post-traumatic osteoarthritis: may develop years later after intra-articular fractures; ankle fusion (arthrodesis) or total ankle replacement may become necessary
- Persistent swelling and stiffness; chronic pain
- Chronic instability (particularly where there was an associated ligament injury)
- Leg length discrepancy (rare, mostly after pilon fractures)
Implant-related Problems
- Implant irritation close to the skin: plates over the lateral malleolus may be irritating in patients with thin skin
- Need for implant removal: in approximately 10–20% of patients; usually performed after 9–12 months, once fracture healing is complete
- Syndesmotic screws: removal at 8–12 weeks is debated; flexible fixation systems do not require removal
Factors that Increase Risk
- Smoking (markedly increases the risk of wound healing problems, non-union and infection)
- Poorly controlled diabetes (impaired wound healing, risk of Charcot joint)
- Osteoporosis (poor implant purchase, secondary displacement)
- Peripheral vascular disease and peripheral neuropathy
- Immunosuppressive therapy and rheumatological disease
- Advanced age, obesity
- Open fracture or high-energy injury
- Active or recently treated infection
Contact Your Doctor Immediately If You Have
- Sudden increase in pain or swelling
- Fever above 38 °C
- Discharge, malodour or separation of the wound
- Increasing numbness, tingling or weakness in the foot or toes
- Bruising, coldness or pallor of the toes (suspected vascular problem)
- Firm, one-sided swelling and redness of the leg (suspected DVT)
- Shortness of breath or chest pain (suspected pulmonary embolism)
- Excessive tightness or unbearable pain within the cast or boot (suspected compartment syndrome)
- Wound edge separation or exposed hardware
Long-term Outcomes
With accurate diagnosis, appropriate treatment and compliant rehabilitation, the great majority of ankle fractures heal without problems. Most patients return to daily activities within 3–4 months and to sport within 4–8 months. Complete recovery may take 1–2 years in some cases; swelling and stiffness may persist for 12 months, particularly after pilon and trimalleolar fractures.
Stopping smoking, controlling blood glucose and maintaining a healthy weight are critical factors for healing and long-term outcome.
Rehabilitation
Rehabilitation after an ankle fracture is the most important part of recovery. The aims are to control swelling and pain, restore joint range of motion, regain muscle strength and balance, and return the patient to daily life and sporting activity. The protocol is individualised according to the type of treatment, the stability of the fracture and the patient's general condition.
Rehabilitation After Non-operative Treatment
- Weeks 0–2: Short leg cast or walking boot. No weight bearing; transfers with crutches. Toe movement, hip and knee range-of-motion exercises. Ice, elevation, swelling control.
- Weeks 2–6: With the surgeon's permission, transition from cast to walking boot; graduated partial weight bearing begins. Hip and knee strengthening continues.
- Weeks 6–8: Cast/boot removed; progression to full weight bearing. Active and passive ankle range-of-motion exercises (dorsiflexion, plantarflexion, inversion, eversion). Calf stretching, intrinsic foot strengthening, gait normalisation.
- Weeks 8–12: Strengthening intensifies (resistance band, heel raises, chair/wall squats). Balance and proprioception exercises. Stationary cycling and swimming are recommended.
- Months 3–4: Straight-line jogging may begin (with the surgeon's permission). Advanced strengthening; single-leg balance work.
- Months 4–6: Sport-specific drills; pivoting, cutting and jumping. Return to low-contact sport.
- Months 6–12: Full return to contact and high-impact sport with the surgeon's approval and once functional criteria are met.
Rehabilitation After Surgery (ORIF)
- Weeks 0–2: Short leg cast or walking boot. No weight bearing; crutches. Toe, hip and knee range-of-motion exercises. Ice, elevation, swelling control. Suture removal at days 10–14.
- Weeks 2–6: Transition from cast to walking boot; early ankle motion may be started with stable fixation. Partial weight bearing usually begins at weeks 4–6.
- Weeks 6–8: Walking boot removed; progression to full weight bearing. Active and passive range of motion. Calf stretching, intrinsic foot strengthening, gait normalisation. If a syndesmotic screw is present, the decision on removal is made in this period.
- Weeks 8–12: Strengthening intensifies (resistance band, heel raises, squats). Balance and proprioception. Stationary cycling, swimming.
- Months 3–5: Light jogging, advanced strengthening, single-leg balance. Introduction of plyometric exercises.
- Months 5–8: Sport-specific drills; pivoting, cutting, jumping. Return to low-contact sport.
- Months 6–12: Full return to contact sport. In complex cases such as pilon fractures, complete recovery may take 12–16 months.
Criteria for Return to Sport and Activity
- Full, pain-free ankle range of motion (dorsiflexion ≥ 10° in particular)
- Calf and intrinsic foot strength at least 85–90% of the opposite leg
- Single-leg heel raise test: at least 25 repetitions
- Single-leg balance tests (30 seconds with eyes closed)
- 90% symmetry on single-leg hop tests
- No swelling or pain after activity
- Control of pivoting, cutting and landing technique
- Approval of the surgeon and physiotherapist
Recommended Activities
- Walking, stationary cycling, elliptical trainer
- Swimming (once the wound has healed)
- Low-impact conditioning and strengthening exercise
- Pilates and yoga (with the surgeon's permission)
- Straight-line running (from month 3–4, with the surgeon's permission)
Activities to Avoid in the First 3–6 Months
- Jumping and high-impact activity
- Running on uneven ground
- Sports involving pivoting and cutting (football, basketball, etc.)
- Heavy lifting (particularly on tiptoe)
- Contact sport
Lifestyle and Recovery Advice
- Perform your home exercise programme every day — it is the single most important determinant of long-term outcome
- Do not smoke (markedly increases the risk of non-union, wound healing problems and infection)
- Maintain tight blood glucose control if you have diabetes
- Healthy weight: every excess kilogram places additional load on the ankle
- Keep the leg elevated above heart level for the first 3 months
- Use ice, compression stockings and other measures to reduce swelling regularly for 3–6 months
- Fall prevention: remove hazards such as rugs and cables at home; use a night light and grab rails in the bathroom
- Attend your follow-up appointments (weeks 4–6, month 3, month 6, year 1)
Expected Outcomes
Most patients return to pain-free daily activity 3–4 months after treatment of an ankle fracture. Mild swelling and stiffness may persist for 6–12 months; this is expected and treatable. Return to sport and high-demand activity occurs between months 4 and 12; recovery may take longer after complex fractures such as pilon and trimalleolar injuries.
Patient satisfaction is high with modern treatment methods and disciplined rehabilitation; anatomical reduction and appropriate rehabilitation reduce the long-term risk of post-traumatic arthritis.
Is This Treatment Right for You?
Every patient's condition is different. After a detailed examination and imaging, the treatment plan that suits you best will be prepared.
Would you like more information about Ankle Fracture?
Book Appointment